
Navicular Stress Fracture: The High-Risk Midfoot Injury X-rays Miss
A navicular stress fracture is a crack in the keystone bone of the arch caused by repeated loading, mostly in sprinters, jumpers and court-sport athletes. It is a high-risk stress fracture: plain X-rays often look normal, so CT or MRI is used, and it heals best with early, strict time off weight bearing.
Common Symptoms
- A vague ache on the top of the midfoot or along the inner arch during sprinting, jumping or cutting
- Pain that fades quickly with rest, so it is easy to dismiss as a sprain or a tight tendon
- Pinpoint tenderness on the top of the navicular bone, a spot known as the N spot
- Pain on hopping on the affected foot or rising onto the toes on that side
- Little or no visible swelling or bruising, even after weeks of symptoms
- Midfoot pain that keeps returning each time training is resumed
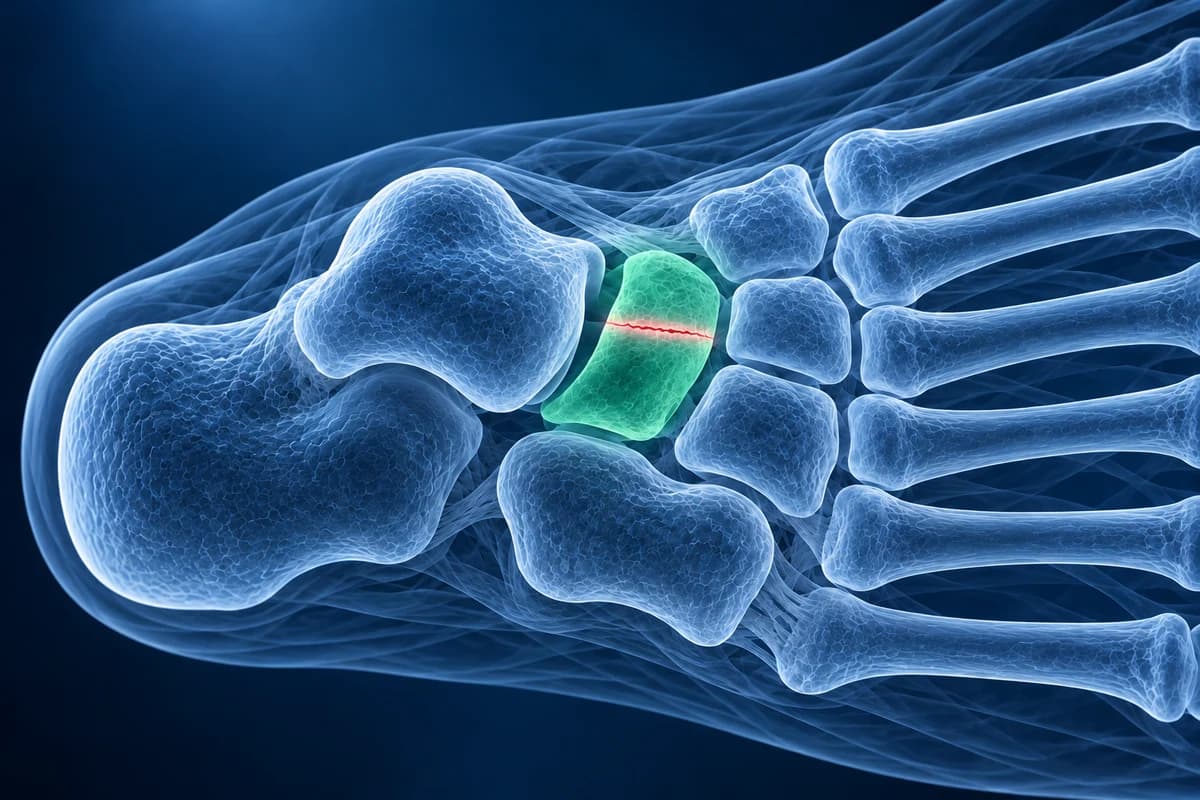
The central third of the navicular is a watershed area where blood vessels from both sides barely meet, and it is also where push-off forces concentrate. That combination explains why these fractures heal slowly, why delayed union and non-union are real risks, and why the diagnosis is often made months late. This page explains how the fracture is found, what the CT and MRI wording means, and why treatment is stricter than for most foot stress fractures. It is educational guidance, not a diagnosis.
Why is a navicular stress fracture called high risk?
Sports medicine sorts stress fractures by how likely they are to heal with simple rest. Most stress fractures heal with rest from the activity that caused them. In the classification by Boden and Osbahr, the navicular sits with the fifth metatarsal and the front of the shin bone in the high-risk group, because poor blood supply and high load make delayed healing, non-union, a complete fracture or, rarely, death of part of the bone more likely if the injury is missed or loaded too early. The StatPearls review on navicular fractures highlights non-union and osteonecrosis as the main concerns.
The practical consequence is that a suspected navicular stress fracture is not treated with “rest it and see” in the way a sore second metatarsal might be. A metatarsal stress fracture usually heals in a stiff shoe, and the Jones fracture page explains the other high-risk foot site.
When should midfoot pain be checked promptly?
- Midfoot pain in a runner or jumper that has lasted more than a couple of weeks and returns with each session
- Sudden worsening, a crack felt during sport, or new inability to bear weight on a foot that was already sore
- Pain across the top of the midfoot after a twist, with bruising on the sole, which needs urgent X-rays
- A warm, swollen midfoot in someone with diabetes and reduced feeling in the feet
The last two are covered on the Lisfranc injury and Charcot foot pages and need same-day assessment.
What is the N spot, and why does it matter?
The N spot is a small area on the top of the navicular, roughly 2 cm in front of the tip of the inner ankle bone and just to the outer side of the tibialis anterior tendon that stands out when you pull the foot up. Pressing there sits directly over the central third of the bone. In the review by Younis and colleagues, focal tenderness at the N spot is described as the most reliable examination sign.
Because the pain is vague and settles quickly with rest, it is often labelled a midfoot sprain or tendon problem. The same review reports an average delay from first symptoms to diagnosis ranging from about four months to more than a year. An athlete with N spot tenderness and a normal X-ray should not be reassured by the X-ray alone.
Why is my X-ray normal if I have a navicular stress fracture?
The fracture usually starts as a thin crack running front to back through the top of the bone, in a plane that standard foot X-rays view side-on or obliquely, and the navicular overlaps with its neighbours. Younis and colleagues cite X-ray sensitivity as low as 33%. X-rays are still taken first, as the ACR Appropriateness Criteria for stress fractures recommend, because they rule out other problems and occasionally show a late fracture with sclerotic edges. The broader story is in why stress fractures do not show on X-ray.
When X-rays are normal and the suspicion remains, the ACR criteria place MRI next. MRI shows early bone marrow edema, before a crack forms, and separates a stress reaction from a complete fracture. CT is the test that shows the fracture line best: it defines how far the crack runs, whether the edges have become sclerotic or cystic, and later whether bone is bridging the gap. The Younis review describes MRI as the preferred test when suspicion is high and CT as the gold standard for characterising a confirmed fracture. You can scroll through either study privately in the free MRI viewer or the free CT viewer.
What does “stress fracture of the tarsal navicular” mean on a CT or MRI report?
These are the phrases most often printed, each with a question to take to your clinician.
- “Bone marrow edema in the navicular without a fracture line”: a stress reaction, the stage before a crack. Ask whether this still needs a period off weight bearing, given that the navicular is a high-risk site.
- “Linear low signal in the central third of the navicular” on MRI: a true stress fracture line. Ask whether a CT is needed to see how far it extends.
- “Dorsal cortical break” or “incomplete fracture”: the crack involves only the top surface, type I in the CT classification by Saxena and colleagues. Ask how long you will be non-weight-bearing and how healing will be checked.
- “Fracture extends into the navicular body” or “complete fracture”: types II and III, with type III reaching the opposite surface. In Saxena's series type III took the longest to heal. Ask whether surgery is being considered.
- “Sclerotic margins”, “cystic change” or “avascular segment”: signs that the fracture has been present for a while and healing is struggling. Ask whether these change the advice between cast treatment and fixation.
For other midfoot wording, see foot MRI report phrases explained.
What We Look For on Navicular Imaging
- Bone marrow edema in the navicular on fluid-sensitive MRI images
- A fracture line in the central third and whether it starts at the dorsal surface
- Extension of the fracture into the body or through to the opposite surface on CT
- Sclerosis, cysts or fragmentation along the fracture edges suggesting delayed union
- Bridging bone across the gap on follow-up CT
- Look-alikes such as an accessory navicular, tendon disease or a bony bar between tarsal bones
How is a navicular stress fracture treated?
For a fracture that is not displaced, the standard first treatment is strict non-weight-bearing in a cast or boot, usually for at least six weeks, followed by a graded return guided by the N spot no longer being tender. The evidence for strict offloading is strong. Khan and colleagues followed 86 CT-proven fractures: 19 of 22 athletes (86%) treated first with a non-weight-bearing cast returned to sport, compared with 9 of 34 (26%) who kept walking on the foot with reduced activity. A later meta-analysis by Torg and colleagues found successful outcomes in 96% with non-weight-bearing treatment and 82% with surgery, while treatment that allowed weight bearing did significantly worse than either.
Surgery with screws, sometimes with bone graft, is considered for displaced or complete fractures, for fractures that have not healed with a full course of offloading, and sometimes for elite athletes after a shared discussion of the trade-offs. Healing on CT can lag behind how the foot feels, so return to sport is judged on the examination as well as the scan. The right plan for you is a decision for your foot and ankle specialist.
What else causes pain over the navicular?
A tender bump on the inner side of the navicular, rather than the top, is often an accessory navicular. In a young child, a flat, dense navicular on X-ray is usually Köhler disease, which heals on its own. Pain along the inner ankle and arch can come from the posterior tibial tendon, and a stiff, painful flat foot in a teenager can be a tarsal coalition. MRI separates these more reliably than X-ray. Use top-of-foot pain and lumps to compare the navicular symptom pattern.
Frequently Asked Questions
Can a navicular stress fracture be missed on X-ray?
Yes, frequently. Sensitivity of X-ray has been reported as low as 33%, so a normal X-ray does not rule it out. If the N spot is tender in an athlete, MRI or CT is usually the next step.
Is MRI or CT better for a navicular stress fracture?
They answer different questions. MRI picks up early bone stress before a crack forms and shows nearby soft tissue. CT shows the fracture line itself most clearly, how far it runs and whether it is healing. Many patients have MRI first and CT if a fracture is found or surgery is considered.
Can I walk on a navicular stress fracture?
Usually not at first. Studies show that continuing to walk on the foot, even with reduced sport, heals far less reliably than a period of strict non-weight-bearing. Follow the plan your clinician sets, even if the pain has settled.
How long until I can run again?
It usually takes months rather than weeks. In Saxena's CT series, return to activity averaged about three to three and a half months for partial fractures and close to seven months for fractures that crossed the whole bone. Your timeline depends on the fracture type and how healing progresses.
Can AI find a navicular stress fracture on my scan?
MRI shows stress-related marrow changes and CT can define a fracture line, alongside examination of the painful area. AI cannot exclude a navicular stress fracture or set a treatment plan.
Sources
- Younis Z, Ravi B, Rezk K, Shah J, Hamid MA. Navicular Stress Fractures: A Narrative Review of Pathoanatomy, Diagnostic Pitfalls, and Management. Cureus. 2025;17(11):e97078.
- Khan KM, Fuller PJ, Brukner PD, Kearney C, Burry HC. Outcome of conservative and surgical management of navicular stress fracture in athletes. Eighty-six cases proven with computerized tomography. Am J Sports Med. 1992;20(6):657-666.
- Torg JS, Moyer J, Gaughan JP, Boden BP. Management of tarsal navicular stress fractures: conservative versus surgical treatment: a meta-analysis. Am J Sports Med. 2010;38(5):1048-1053.
- Saxena A, Fullem B, Hannaford D. Results of treatment of 22 navicular stress fractures and a new proposed radiographic classification system. J Foot Ankle Surg. 2000;39(2):96-103.
- Boden BP, Osbahr DC. High-risk stress fractures: evaluation and treatment. J Am Acad Orthop Surg. 2000;8(6):344-353.
- Expert Panel on Musculoskeletal Imaging; Morrison WB, Deely D, Fox MG, et al. ACR Appropriateness Criteria Stress (Fatigue-Insufficiency) Fracture Including Sacrum Excluding Other Vertebrae: 2024 Update. J Am Coll Radiol. 2024;21(11S):S490-S503.
- Gheewala R, Arain A, Rosenbaum AJ. Tarsal Navicular Fractures. StatPearls. Treasure Island (FL): StatPearls Publishing.
Understand your imaging before your next appointment
MRI, X-ray or CT from a CD, folder or ZIP. A PDF report or photos of the films work too.
Free to open and preview, no account needed. An optional AI report from $10 explains your images in plain language, with questions for your doctor.
Your raw files stay on this device. Only rendered images and minimal context are sent when you request an AI report.
Medical Disclaimer: This page is for informational and educational purposes only. It does not constitute medical advice, diagnosis, or treatment. AI-generated analysis may contain errors. Always consult a qualified healthcare professional for medical decisions. Full Disclaimer