
Charcot Foot (Charcot Neuro-Osteoarthropathy): Urgent Signs and Imaging Explained
Charcot foot, or Charcot neuro-osteoarthropathy, is a breakdown of the bones and joints of a foot that has lost normal feeling, most often because of diabetic nerve damage. In the active stage the foot turns warm, swollen and red, yet often hurts far less than it looks. X-rays can still be normal in the first weeks, while MRI already shows bone marrow edema. Prompt offloading in a knee-high cast or device is what protects the shape of the foot.
Some signs described on this page need prompt medical care. If you have them, get care first. Reading about imaging can wait.
When should a hot, swollen foot be seen the same day?
If you have diabetes or reduced feeling in your feet and one foot is suddenly warmer, redder or more swollen than the other, contact your diabetes foot team, GP or urgent care today. Do not wait for a routine appointment, an MRI slot or an online result, and keep weight off that foot until you have been examined.
- Go to the emergency department now if the hot foot comes with fever, chills, feeling generally unwell, very high blood sugars, or redness that is spreading up the leg.
- Seek same-day care if there is any open wound, blister, drainage or bad smell on the swollen foot: infection must be ruled out before anything else.
- Seek same-day care if the shape of the foot or ankle seems to be changing, the arch is dropping, or the foot feels unstable, even when it barely hurts.
- A swollen calf as well as a swollen foot can be a blood clot, which also needs urgent assessment.
This page explains the condition and the words your X-ray or MRI report may use. It is educational and is not a diagnosis: only a clinician who examines your foot, checks the skin and compares the temperature of both feet can decide whether you have active Charcot, an infection, or something else.
Common Symptoms
- One foot noticeably warmer than the other when both are felt with the back of the hand
- Swelling of the midfoot or ankle that appears without a clear injury, or after a minor stumble
- Redness over the top or inner side of the foot with the skin still intact
- Little or no pain compared with how swollen the foot looks, because of numbness from neuropathy
- A flattening arch, a bump on the sole, or shoes that suddenly no longer fit
- A feeling that the foot or ankle is loose or wobbly when standing
Why does Charcot foot happen if it barely hurts?
Pain normally makes us limp, rest and protect an injured foot. When peripheral neuropathy has dulled that warning system, small sprains and hairline fractures go unnoticed and the person keeps walking on them. The injury sets off an intense local inflammatory response, blood flow to the bone increases, the bone softens, and more fractures and joint dislocations follow. Diabetes is by far the most common cause in high-income countries, but any condition that removes protective sensation, such as alcohol-related neuropathy or nerve damage after chemotherapy, can lead to the same process.
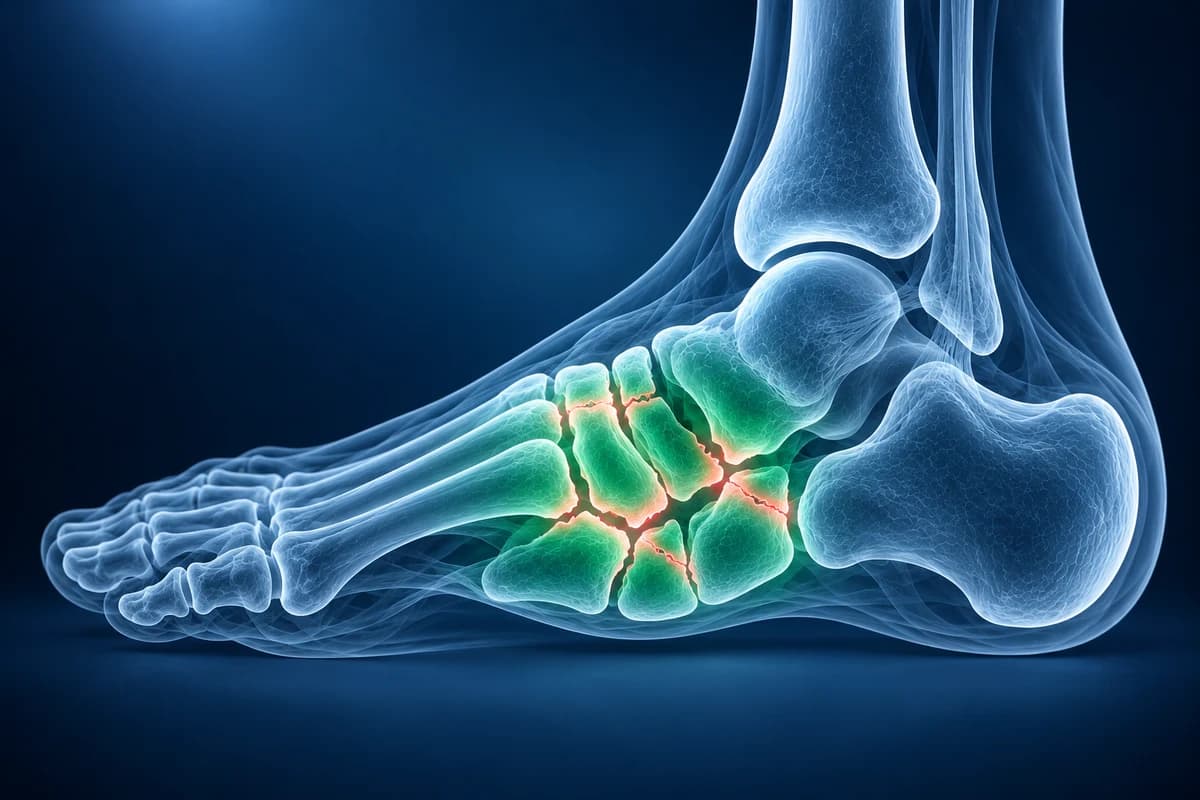
The midfoot is the classic site, especially the tarsometatarsal joints (the Lisfranc joint line) and the joints around the navicular. The hindfoot and ankle can be involved too. Left untreated, the arch can collapse into a rocker-bottom foot, where the sole bulges downward. That bony prominence then takes all the pressure of walking, which is how Charcot leads to ulcers, deep infection and, in the worst cases, amputation. Catching the active stage early is the single most important step in preventing that chain.
Is it Charcot, an infection, gout or a blood clot?
A red, hot, swollen foot in someone with diabetes has several possible causes, and they need very different treatment. Cellulitis and bone infection, gout, a deep vein thrombosis and an unrecognised fracture can all look alike at first. International diabetic foot guidance (IWGDF 2023) asks clinicians to always consider active Charcot when a person with diabetes and neuropathy has a warmer, swollen or red foot compared with the other side and the skin is intact, and to start knee-high offloading while the other causes are being ruled out. For broader symptom descriptions, see top-of-foot pain and lumps; this does not replace urgent Charcot assessment.
The state of the skin is one of the most useful clues. Bone infection in a diabetic foot almost always spreads inward from an ulcer or wound, so intact skin makes it less likely, while an ulcer over the swollen area means infection has to be actively excluded. Read more on diabetic foot osteomyelitis and on gout in the foot, which can also cause a sudden hot joint. Blood tests such as CRP or ESR are not reliable for diagnosing Charcot on their own, and the guideline advises against relying on them for that purpose.
Many foot clinics measure skin temperature on both feet with an infrared thermometer at the same spots. A difference of around 2 °C or more between the feet is widely used as a sign of active disease, and the same readings are repeated over the following months to track whether the inflammation is settling.
Which scan comes first: X-ray or MRI?
Plain X-ray comes first. Guidance recommends standing X-rays of the foot and ankle in three views (front, oblique and side), ideally of both feet so the radiologist can compare them. Standing films show collapse and malalignment that can be hidden when the foot is not bearing weight. If the X-rays look normal but the foot is still warm and swollen, MRI is recommended to confirm or exclude active Charcot, because the earliest stage shows up only as bone marrow edema and small fractures that X-ray cannot see. Where MRI is not possible, a nuclear medicine scan, CT or SPECT-CT can support the diagnosis.
You can open your own images in the free foot X-ray viewer or the free foot MRI viewer to follow along with your report. Our guides on how to read a foot X-ray, how to read a foot MRI and foot MRI vs X-ray vs ultrasound explain the views and sequences. The X-ray report glossary explains terms accompanying Charcot-related alignment changes.
What does my Charcot report wording mean?
- “Bone marrow edema in multiple midfoot bones”: extra fluid inside several neighbouring bones, a sign of active inflammation and microfractures. In Charcot it typically centres on the joints and spreads across several bones rather than sitting under a single ulcer.
- “Subchondral fracture”: a crack in the bone just beneath the joint cartilage, often seen on MRI as a dark line inside a bright cloud of edema.
- “Fragmentation” or “osseous debris”: small pieces of broken bone around the joints, typical of the destructive phase.
- “Subluxation at the tarsometatarsal (Lisfranc) joints”: the metatarsals have shifted out of line with the midfoot bones. The same joint line is injured in a traumatic Lisfranc injury, but in Charcot it happens without a major accident.
- “Loss of the longitudinal arch” or “rocker-bottom deformity”: the arch has collapsed and the midfoot now sags toward the ground, raising pressure on the sole.
- “Neuropathic arthropathy” or “findings compatible with neuro-osteoarthropathy”: the radiologist's way of saying the pattern fits Charcot. Your clinician still has to combine it with the examination.
What We Look For on Imaging
- Joint-centred bone marrow edema involving several adjacent midfoot or hindfoot bones on STIR or T2 MRI
- Subchondral fractures, cortical breaks and joint effusions across the tarsometatarsal or midtarsal joints
- Fragmentation, bone debris and periarticular soft tissue swelling on standing X-rays
- Malalignment such as Lisfranc subluxation, a dropped talus or reversal of the normal arch on the lateral view
- Comparison with earlier studies to tell new destruction from older, consolidated changes
- Any skin ulcer, sinus tract or fluid collection that would raise concern for superimposed infection
What are the stages of Charcot foot?
The traditional Eichenholtz system describes how the foot moves through the disease. Stage 0 is the earliest: the foot is hot and swollen, X-rays look normal and MRI shows marrow edema. Stage 1, fragmentation, brings visible fractures, debris and joint dislocation. Stage 2, coalescence, is when the swelling starts to settle and the fragments are reabsorbed. Stage 3, consolidation or reconstruction, is a cool, stable foot, sometimes with a permanent deformity.
Current diabetic foot guidance uses a simpler split: active Charcot, with signs of inflammation, and Charcot in remission, where the inflammation has gone and any fractures have consolidated on X-ray. Remission is judged by combining the temperature difference between the feet, the swelling, and imaging, rather than any single test. Charcot can become active again, so the foot needs long-term follow-up even in remission.
How is active Charcot foot treated?
The foundation is immobilising and offloading the foot in a knee-high device as soon as active Charcot is suspected. A total contact cast is the usual first choice, changed regularly by the foot team; a knee-high walker boot made non-removable is the second option, and a removable boot worn at all times is a third choice when the others are not tolerated. Ordinary shoes, post-operative sandals and other below-the-ankle devices are not recommended for the active stage because they do not hold the injured joints still. Crutches, a frame or a knee scooter help reduce weight on the affected leg.
Treatment usually lasts many months, and the cast or boot comes off only when the foot team agrees the disease is in remission. Bone drugs such as bisphosphonates or calcitonin are not recommended to treat active Charcot under the 2023 guideline. Once the foot is stable, custom shoes or orthoses that fit its new shape help prevent ulcers and reactivation. Surgery is considered when the foot or ankle stays unstable, when a deformity is likely to cause an ulcer, or when the foot cannot be held safely in a cast.
A slow, painless arch collapse in a person without neuropathy is a different problem; see flat foot. A single sore metatarsal after more walking than usual may be a metatarsal stress fracture instead, although in a numb foot that can also be the first step toward Charcot.
What should I ask my foot team?
- Is this active Charcot, and how sure are we that infection, gout or a clot has been ruled out?
- Which joints are involved, and is there any dislocation or collapse on the standing X-rays?
- Does the MRI show marrow edema spread around the joints, or is it focused under a wound, which would worry you more about bone infection?
- What device will I wear, how often will it be checked, and how will we know when it can come off?
- Should my other foot be checked, and what footwear will I need afterwards?
Frequently Asked Questions
Can Charcot foot show up on MRI before it shows on X-ray?
Yes. In the earliest active stage the X-rays can look completely normal while MRI already shows bone marrow edema, small subchondral fractures and joint fluid in the midfoot. That is why guidance recommends MRI when the foot is warm and swollen but the X-rays are normal. A normal X-ray does not mean the foot is safe to walk on.
How do doctors tell Charcot foot from a bone infection on MRI?
They look at the pattern and the skin. Charcot tends to cause edema around several joints in the midfoot with intact skin, while bone infection usually sits directly beneath an ulcer or sinus tract, often at the toes, metatarsal heads or heel. The two can overlap, and infection can develop in a Charcot foot that already has an ulcer. When the picture stays unclear, a bone biopsy may be needed. Treat this as a question to discuss with your team, not something to decide from the report alone.
How long does it take for Charcot foot to settle?
Most people need offloading for many months, and the time varies widely with the joints involved, how early treatment started and how strictly weight was kept off the foot. Remission is confirmed by your team using repeated temperature checks, the swelling and imaging together, not by a set number of weeks.
Can I walk on a Charcot foot if it does not hurt?
Lack of pain is part of the problem, not a sign of safety. Walking on an active Charcot foot outside a protective device can drive further fractures and collapse. Follow the weight-bearing advice of the clinician who fitted your cast or boot.
Can AI diagnose Charcot foot from my scan?
Charcot assessment needs an examination, temperature comparison and imaging; a hot, swollen foot needs same-day care. AI cannot diagnose Charcot or replace that assessment.
Sources
- Wukich DK, Schaper NC, et al. Guidelines on the diagnosis and treatment of active Charcot neuro-osteoarthropathy in persons with diabetes mellitus (IWGDF 2023). Diabetes Metab Res Rev. 2024;40(3):e3646.
- Rogers LC, Frykberg RG, Armstrong DG, et al. The Charcot foot in diabetes. Diabetes Care. 2011;34(9):2123-2129.
- Collins AC, Bergman R. Charcot Neuropathic Osteoarthropathy. StatPearls. Treasure Island (FL): StatPearls Publishing.
- American College of Radiology. ACR Appropriateness Criteria: Suspected Osteomyelitis of the Foot in Patients With Diabetes Mellitus.
Related Articles
Why a diabetic foot X-ray comes first, when MRI is used to tell bone infection from Charcot foot, and why scans alone do not decide treatment.
A plain-language guide to your foot MRI: how T1, fluid-sensitive and STIR images differ, which plane shows what, and what bone marrow edema, plantar plate tear and neuroma mean in your report.
Do not delay urgent medical care to use this tool.
After you get care, understand your imaging
MRI, X-ray or CT from a CD, folder or ZIP. A PDF report or photos of the films work too.
Free to open and preview, no account needed. An optional AI report from $10 explains your images in plain language, with questions for your doctor.
Your raw files stay on this device. Only rendered images and minimal context are sent when you request an AI report.
Medical Disclaimer: This page is for informational and educational purposes only. It does not constitute medical advice, diagnosis, or treatment. AI-generated analysis may contain errors. Always consult a qualified healthcare professional for medical decisions. Full Disclaimer