
Diabetic Foot Osteomyelitis: When to Get Help and What Imaging Shows
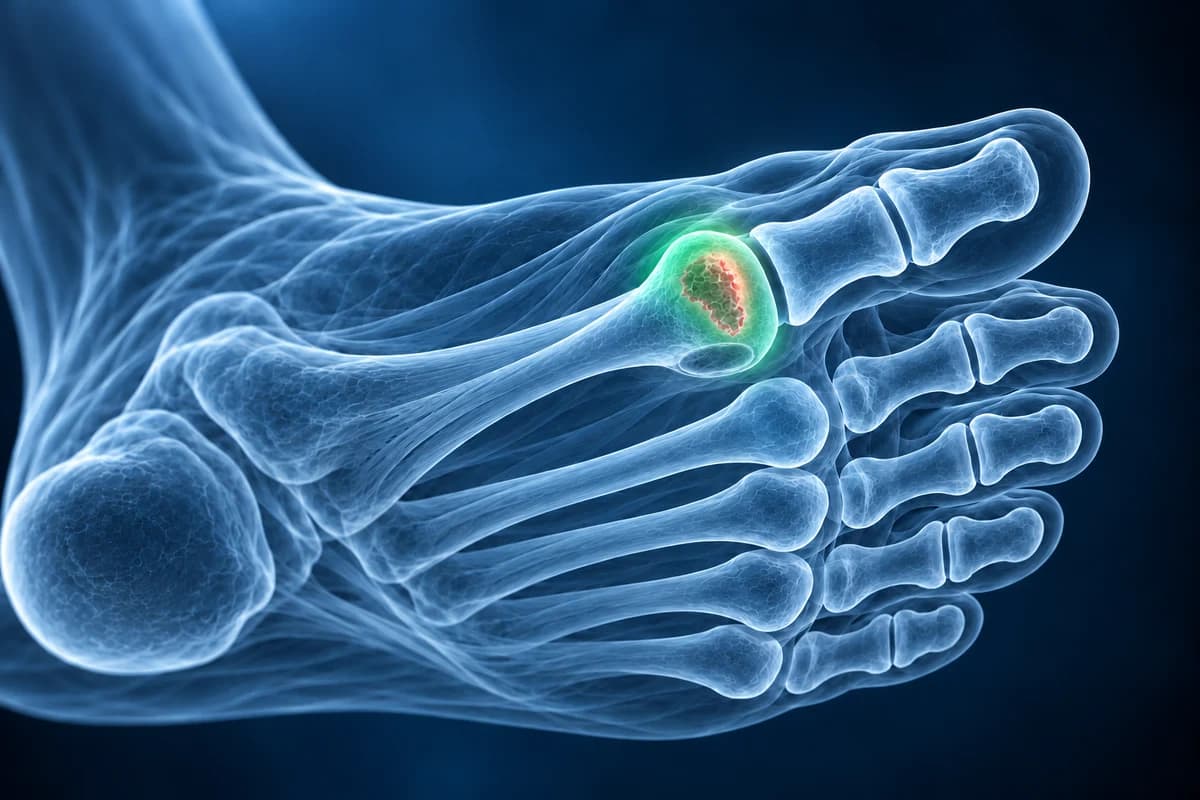
Diabetic foot osteomyelitis is an infection of bone in the foot of a person with diabetes. It almost always starts in an ulcer and spreads inward to the bone below, most often at the toes, the metatarsal heads or the heel. Doctors usually begin with a probe-to-bone test, a foot X-ray and blood markers, add MRI when the answer is still unclear, and treat with antibiotics, surgery, or both.
Some signs described on this page need prompt medical care. If you have them, get care first. Reading about imaging can wait.
When is a diabetic foot wound an emergency?
A foot infection in a person with diabetes can spread quickly and threaten the leg. Go to the emergency department today if you have a foot wound together with any of the signs below. Do not wait for a scan, a routine clinic or an online opinion.
- Fever, chills, a racing heart, fast breathing, confusion or feeling suddenly very unwell
- Redness, heat or swelling that is spreading away from the wound or up the foot and leg
- Pus, a foul smell, black or grey skin, or a crackling feeling under the skin when it is pressed
- A foot or toes that have turned pale, blue or cold, or new severe pain in a foot that is usually numb
- Blood sugars that are suddenly much higher than usual and will not come down
Any open wound on a diabetic foot that is not clearly healing, or that you can see bone at the bottom of, should be seen by your diabetes foot team, GP or podiatrist within a day, even without these signs.
This page explains how the diagnosis is made and what the phrases on an X-ray or MRI report mean, so you can talk it through with your care team. It is not a diagnosis and cannot replace an examination of the wound, the circulation and the rest of the foot.
Common Symptoms
- A foot ulcer that has been open for weeks, is deep, or sits over a bony point such as a toe joint or heel
- Bone that can be seen or felt at the bottom of the wound
- A red, swollen “sausage” toe next to or under an ulcer
- Drainage, odour or a wound that keeps reopening despite good offloading and dressings
- Warmth and swelling around the ulcer, sometimes with surprisingly little pain because of neuropathy
- Fever, raised blood sugars or feeling unwell when the infection is spreading
How does a foot ulcer turn into a bone infection?
Neuropathy removes the pain that would normally warn of a blister or pressure sore, and reduced circulation slows healing. Bacteria that colonise the ulcer can track down through the soft tissue until they reach bone. The risk rises when an ulcer has been present for many weeks, is wide or deep, sits over a bony prominence, exposes bone, or comes with a swollen, red toe. Bone infection makes amputation more likely, which is why it is taken seriously even when the wound looks small on the surface.
Peripheral artery disease often travels with diabetes and changes the plan. An infected foot with poor blood flow needs both a surgical and a vascular opinion urgently, because antibiotics and surgery work poorly in tissue that does not get enough blood.
How do doctors diagnose osteomyelitis in a diabetic foot?
The 2023 IWGDF/IDSA guideline suggests starting with a combination of three things: a probe-to-bone test, plain X-rays of the foot, and a blood inflammatory marker such as ESR, CRP or procalcitonin. In the probe-to-bone test the clinician gently passes a sterile blunt metal probe into the wound; feeling hard, gritty bone makes osteomyelitis more likely. No single test settles the question, so the results are read together.
When the diagnosis is still in doubt, the guideline strongly recommends MRI. PET-CT, white blood cell scintigraphy or SPECT are alternatives when MRI cannot be done. The most definitive test is a bone sample, taken in theatre or through the skin, which confirms infection and identifies the bacteria so the antibiotic can be matched to them. Swabs from the surface of the wound often grow different organisms from the bone.
The ACR Appropriateness Criteria follow the same order for imaging: X-ray first, then MRI when the X-rays are negative or unclear, or when surgery is being planned. Ultrasound is not useful for judging bone infection in this setting. To compare the tests in plain words, see foot MRI vs X-ray vs ultrasound, and for what to expect when booking, see foot MRI cost.
Why can the first X-ray look normal?
X-ray only shows osteomyelitis once enough bone has been destroyed to change its outline or density, and that usually lags behind the infection by a couple of weeks. A normal first X-ray therefore does not rule it out. Comparing a repeat X-ray a few weeks later with the first one, side by side, is a common and inexpensive way to spot new bone loss. Gas in the soft tissues on any X-ray is an emergency sign of a severe, gas-forming infection.
You can load both studies into the free foot X-ray viewer to compare them, or open an MRI in the free foot MRI viewer. Our guides on how to read a foot X-ray and how to read a foot MRI explain the views and sequences.
What does my osteomyelitis report wording mean?
- “Confluent low T1 marrow signal”: the normal fatty bone marrow, bright on T1 images, has been replaced by a solid dark area. This is one of the more specific MRI signs that infection has entered the bone.
- “Marrow edema on STIR with preserved T1 signal” or “reactive osteitis”: the bone is irritated by nearby inflammation, but the fatty marrow is still there. Reports often describe this as less specific, and it can also come from Charcot, a fracture or recent surgery.
- “Cortical erosion” or “cortical destruction”: the hard outer shell of the bone has been eaten away, usually right under the ulcer.
- “Periosteal reaction”: new bone laid down along the surface, a response to infection or injury that X-ray can pick up after some weeks.
- “Sinus tract extending to bone”: a channel running from the skin wound down to the bone, which ties the bone changes to the ulcer above them.
- “Abscess”, “rim-enhancing collection” or “soft tissue gas”: a pocket of pus or gas in the soft tissue. These often need prompt drainage or surgery.
What We Look For on Imaging
- Bone marrow changes that sit directly beneath a skin ulcer or sinus tract rather than spread around joints
- Confluent replacement of fatty marrow on T1 images with matching bright signal on STIR or T2
- Cortical erosion, focal bone loss or periosteal reaction on X-ray, compared with earlier studies
- Soft tissue ulcer depth, cellulitis, abscess and sinus tracts on MRI
- Septic arthritis of a nearby toe or metatarsophalangeal joint, with joint fluid and erosions on both sides
- Soft tissue gas on X-ray, which needs emergency surgical assessment
Is it osteomyelitis or Charcot foot?
Both can make a diabetic foot warm and swollen, and both can show marrow edema on MRI, which is why the MRI report sometimes cannot decide between them. Location helps: infection usually sits under an ulcer at the toes, metatarsal heads or heel, while Charcot foot usually involves several joints of the midfoot with intact skin. The two can also coexist when a Charcot foot develops an ulcer. In that situation the guideline notes that marrow edema from Charcot, trauma or surgery lowers how specific MRI is, and a review by an experienced musculoskeletal radiologist or a bone biopsy may be needed. Compare infection-related terminology with the foot MRI report glossary. The midfoot pain and swelling guide provides context, but suspected diabetic foot infection needs prompt clinical care.
Use this as a list of questions for your treating team, not as a way to read your own scan. A hot, swollen joint can also be gout, and a sore metatarsal with marrow edema but no wound may be a metatarsal stress fracture. Only the people examining you can weigh those possibilities.
How is diabetic foot osteomyelitis treated?
Treatment combines several parts: antibiotics chosen from bone culture where possible, removal of infected or dead bone when needed, offloading the wound, controlling blood sugar, and restoring blood flow if the arteries are narrowed. For forefoot osteomyelitis without poor circulation, exposed bone or an abscess needing drainage, antibiotics without surgery can be an option. Severe infections, gangrene, deep abscesses or necrotising infection need urgent surgical review.
The 2023 guideline suggests about 6 weeks of antibiotics when the infected bone is not removed, and up to 3 weeks after a minor amputation when bone at the cut edge still grows bacteria. Because the infection can come back, cure is judged at least 6 months after antibiotics finish, so follow-up continues well after the wound closes.
What should I ask my care team?
- Does the probe reach bone, and how do the X-ray and blood markers fit with that?
- Is the MRI change true marrow replacement, or reactive edema that could have another cause?
- Should a bone sample be taken before or during antibiotics, and which bacteria are we treating?
- Is the blood supply to my foot good enough, and do I need a vascular assessment?
- Will the bone be removed or treated with antibiotics alone, and how will we check it has cleared?
Frequently Asked Questions
Can a normal X-ray rule out osteomyelitis in a diabetic foot?
No. Bone loss usually takes a couple of weeks to become visible on X-ray, so an early film can look normal. If a wound is deep, reaches bone or is slow to heal, your team may repeat the X-ray, order an MRI or take a bone sample.
What does a positive probe-to-bone test mean?
It means a sterile probe passed through the wound touched hard, gritty bone. That makes bone infection more likely, especially in a wound that already looks infected, and doctors combine it with X-ray and blood tests rather than relying on it alone.
How accurate is MRI for diabetic foot osteomyelitis?
MRI is the most studied advanced test and is very sensitive, which is why guidelines recommend it when the diagnosis is uncertain. It is less specific when the bone is also affected by Charcot, a recent fracture or surgery, because those cause similar marrow edema. A bone biopsy remains the most definitive test.
Does osteomyelitis always mean amputation?
No. Many people are treated with antibiotics, with removal of a small amount of infected bone, or both. The risk of a larger amputation rises with delayed care, severe infection and poor circulation, which is why early assessment matters so much.
Can AI tell me if my foot bone is infected?
Bone infection assessment combines wound examination, circulation checks, imaging and sometimes bone samples; warning signs need care today. AI cannot confirm or exclude infection.
Sources
- Senneville É, et al. IWGDF/IDSA guidelines on the diagnosis and treatment of diabetes-related foot infections (IWGDF/IDSA 2023). International Working Group on the Diabetic Foot.
- American College of Radiology. ACR Appropriateness Criteria: Suspected Osteomyelitis of the Foot in Patients With Diabetes Mellitus.
- Donovan A, Schweitzer ME. Use of MR imaging in diagnosing diabetes-related pedal osteomyelitis. RadioGraphics. 2010;30(3):723-736.
- Wukich DK, Schaper NC, et al. Guidelines on the diagnosis and treatment of active Charcot neuro-osteoarthropathy in persons with diabetes mellitus (IWGDF 2023).
Related Articles
Why a diabetic foot X-ray comes first, when MRI is used to tell bone infection from Charcot foot, and why scans alone do not decide treatment.
X-ray, MRI, ultrasound or CT for foot pain? What each test shows and misses, which one usually comes first, and how the choice changes for stress fractures, neuromas, plantar fasciitis, Lisfranc injuries and the diabetic foot.
A plain-language guide to your foot MRI: how T1, fluid-sensitive and STIR images differ, which plane shows what, and what bone marrow edema, plantar plate tear and neuroma mean in your report.
Do not delay urgent medical care to use this tool.
After you get care, understand your imaging
MRI, X-ray or CT from a CD, folder or ZIP. A PDF report or photos of the films work too.
Free to open and preview, no account needed. An optional AI report from $10 explains your images in plain language, with questions for your doctor.
Your raw files stay on this device. Only rendered images and minimal context are sent when you request an AI report.
Medical Disclaimer: This page is for informational and educational purposes only. It does not constitute medical advice, diagnosis, or treatment. AI-generated analysis may contain errors. Always consult a qualified healthcare professional for medical decisions. Full Disclaimer