
Bunion (Hallux Valgus) X-ray: Reading the Angles on Your Report
A bunion is called hallux valgus on an X-ray report. On a standing X-ray it is usually diagnosed when the hallux valgus angle between the big toe and the first metatarsal is above 15° and the intermetatarsal angle between the first and second metatarsals is above 9°. The bigger the two angles, the more severe the deformity, but pain and shoe fit matter more than the number when you and your clinician decide on treatment.
Common Symptoms
- A firm bump on the inner edge of the foot at the base of the big toe that rubs in narrow shoes
- The big toe drifting toward the second toe, sometimes riding over or under it
- Redness, a fluid-filled bursa or a thick callus over the bump after a long day in footwear
- Aching under the ball of the foot beneath the second and third toes as load shifts away from the big toe
- Stiffness or grinding at the big toe joint in long-standing bunions with joint wear
- Numbness or tingling along the inner side of the big toe where a small skin nerve crosses the bump
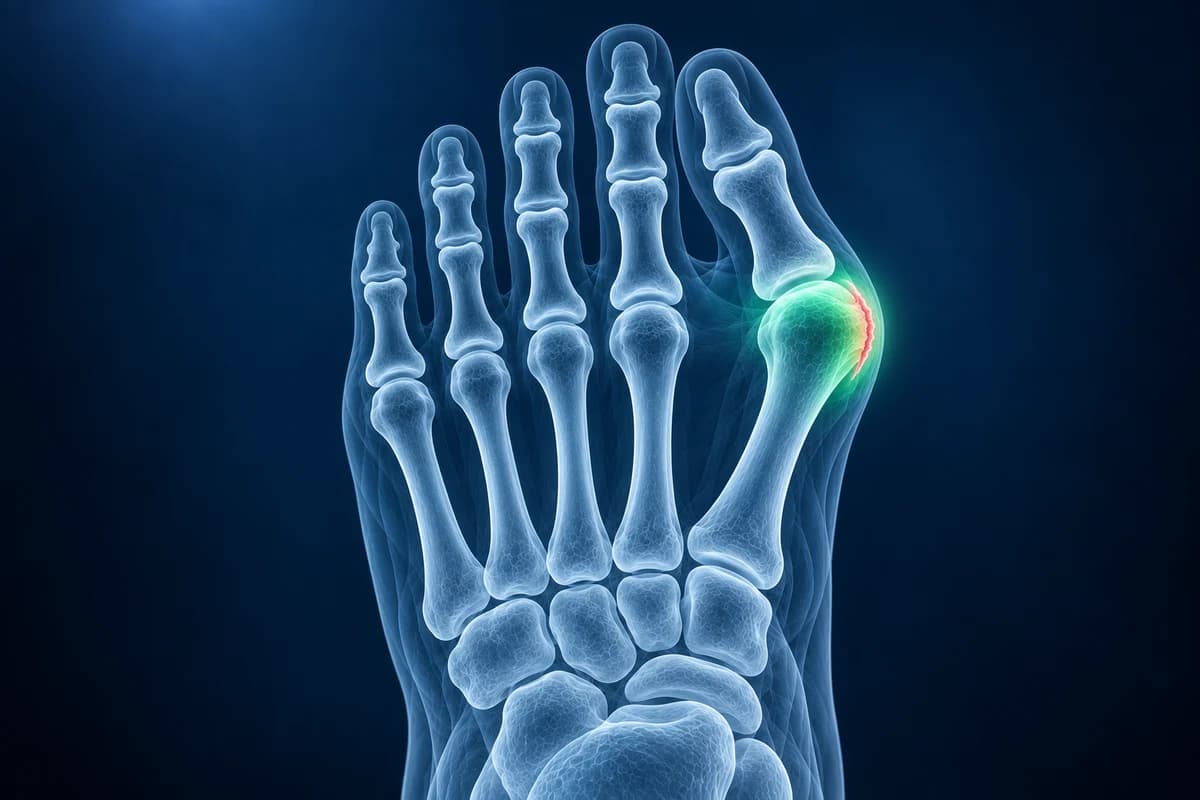
This page explains each measurement a radiologist or foot surgeon writes about a bunion, what the severity bands mean, why the X-ray must be taken while you stand, and when another scan is worth adding. It is educational guidance, not a diagnosis.
What does “hallux valgus angle” mean on an X-ray report?
The hallux valgus angle, often shortened to HVA, is drawn between a line through the middle of the first metatarsal shaft and a line through the middle of the big toe's first bone (the proximal phalanx). In a straight toe the two lines almost line up. As the toe drifts outward toward the second toe, the angle opens. The intermetatarsal angle, or IMA, is drawn between the first and second metatarsal shafts and shows how far the first metatarsal has swung toward the inner edge of the foot. Many reports call that swing “metatarsus primus varus”. The X-ray report glossary puts hallux valgus terminology in context.
Foot surgeons commonly group the deformity using both angles together. One widely used scheme, summarised by Coughlin and Jones, reads as follows:
- Normal: hallux valgus angle below 15° and intermetatarsal angle below 9°.
- Mild: hallux valgus angle up to about 20° with an intermetatarsal angle up to about 11°.
- Moderate: hallux valgus angle roughly 20° to 40° with an intermetatarsal angle roughly 11° to 16°.
- Severe: hallux valgus angle above 40° or an intermetatarsal angle above 16°.
Measurements differ by a few degrees between readers and between X-rays of the same foot, so a change of 2° or 3° from one study to the next is usually within measurement error rather than a real worsening. The step-by-step method for drawing these lines is in the foot X-ray angles guide.
Which other phrases on a bunion report matter?
- “Lateral sesamoid subluxation”: the two small bones under the big toe joint have slid outward with the tendons. Reports may grade the position on a scale; more displacement usually goes with a larger IMA and matters to the surgeon because correcting it is part of the repair.
- “Prominent medial eminence”: the bump itself, the inner edge of the first metatarsal head. Its size explains shoe pressure but does not by itself grade the deformity.
- “Increased distal metatarsal articular angle” (DMAA): the cartilage surface of the first metatarsal head is tilted outward. It hints that the joint surface itself is angled, which can change the type of correction a surgeon plans.
- “Incongruent first MTP joint”: the toe has slid sideways on the metatarsal head so the joint surfaces no longer face each other squarely. A congruent joint is angled but still lined up.
- “Degenerative change of the first MTP joint”: joint-space narrowing or bone spurs, meaning arthritis is present alongside the bunion. That overlap with hallux rigidus can shift treatment away from realignment toward joint-sparing or fusion options.
- “Hallux valgus interphalangeus”: the bend is in the toe itself, between its two bones, rather than at the big toe joint. It can coexist with a classic bunion.
Why does a bunion X-ray have to be taken standing?
Body weight spreads the forefoot and lets the first metatarsal drift into its true resting position. An X-ray taken lying down or with the foot propped on the table can make both angles look smaller than they are when you walk. For that reason bunion assessment and surgical planning use weight-bearing views: a top-down (dorsoplantar or AP) view for the angles, a side view for the arch and joint spurs, and often an oblique view. A tangential sesamoid view is sometimes added to show how the sesamoids sit under the metatarsal head.
If you already have the images, you can open them in the free foot X-ray viewer and check whether the study was weight-bearing; the image header or the report usually says so. For a full walk-through of the other bones on the same film, read how to read a foot X-ray.
What We Look For on Bunion Imaging
- Hallux valgus angle and intermetatarsal angle on a weight-bearing top-down view
- Position of the tibial and fibular sesamoids relative to the first metatarsal head
- Joint congruency and the tilt of the first metatarsal joint surface
- Joint-space narrowing, dorsal or medial spurs and cysts suggesting first MTP arthritis
- Thickened second metatarsal cortex or crowding of the lesser toes from load transfer
- After surgery: osteotomy position, screw or plate placement and signs of bone healing
Do you need an MRI, CT or ultrasound for a bunion?
Usually not. The American College of Radiology Appropriateness Criteria for chronic foot pain place plain radiographs first, and for a typical bunion the standing X-ray answers the questions that guide care. Further imaging is reserved for a specific question the X-ray cannot answer:
- MRI when pain sits under the ball of the foot rather than on the bump, to look for a plantar plate tear at the second toe, a stress reaction in a lesser metatarsal, or sesamoid trouble under the big toe.
- Weight-bearing CT in some centres before surgery, because it shows rotation of the first metatarsal that a flat X-ray can only hint at.
- Ultrasound for a soft, swollen bursa over the bump or to guide an injection.
If you are weighing a scan, the comparison of foot MRI, X-ray and ultrasound sets out what each can and cannot show.
Does a bigger angle mean you need surgery?
No angle on its own makes surgery necessary. Many people live with a moderate bunion that never hurts, and wider shoes, toe spacers, padding over the bump and calf and foot exercises are the usual first steps. Surgery is discussed when pain persists despite these measures or the deformity interferes with walking. Splints and spacers can ease symptoms but do not permanently straighten the bones.
When surgery is planned, the angles help the surgeon choose the procedure. Milder deformities are often corrected by cutting and shifting the end of the first metatarsal, while larger intermetatarsal angles or an unstable first midfoot joint may call for a correction further back in the foot. What an operated foot looks like on follow-up films is covered in bunion surgery X-rays before and after. Compare the other forefoot pain patterns before discussing bunion surgery.
Bunions are common. A systematic review by Nix and colleagues estimated hallux valgus in roughly 23% of adults aged 18 to 65 and about 36% of people over 65, with women affected more often than men.
When should a painful big toe joint be seen urgently?
- The joint turns suddenly hot, red and very swollen, especially overnight. That pattern suggests gout or infection rather than a bunion.
- You have a fever, spreading redness or pus from a sore over the bump.
- You have diabetes or poor circulation and notice a blister, ulcer or open skin over the joint.
- After bunion surgery the toe becomes pale, cold, blue or numb, or the calf swells and aches.
An AI explanation can help you prepare questions for your clinician. It cannot confirm an injury or its grade on its own and is not a diagnosis.
Frequently Asked Questions
What hallux valgus angle counts as a bunion?
A hallux valgus angle above 15° on a standing X-ray is generally regarded as abnormal, usually together with an intermetatarsal angle above 9°. Roughly, up to 20° is mild, 20° to 40° moderate and above 40° severe. Symptoms, not the angle alone, decide whether treatment is needed.
Why do two X-rays of my bunion show different angles?
Angles depend on whether you were standing, how the foot was rotated and where the reader placed the lines. Differences of a few degrees are expected. A non-weight-bearing film usually shows smaller angles than a standing one, so compare like with like.
Can a bunion be fixed without surgery?
Footwear changes, padding, spacers and exercises can relieve pain and pressure, and many people never need an operation. They do not reverse the bone alignment. Surgery is the only way to realign the bones and is usually reserved for persistent pain or functional problems.
Does my bunion report mention arthritis, and why does it matter?
Look for words such as joint-space narrowing, osteophytes or degenerative change at the first MTP joint. Arthritis in the joint changes the options: a realignment procedure may not relieve pain from worn cartilage, and fusion of the joint becomes part of the discussion.
Can AI measure the angles on my bunion X-ray?
Weight-bearing X-rays show the hallux valgus and intermetatarsal angles used to assess a bunion. AI cannot provide validated measurements or choose treatment.
Sources
- Coughlin MJ, Jones CP. Hallux valgus: demographics, etiology, and radiographic assessment. Foot Ankle Int. 2007;28(7):759-777.
- Nix S, Smith M, Vicenzino B. Prevalence of hallux valgus in the general population: a systematic review and meta-analysis. J Foot Ankle Res. 2010;3:21.
- Expert Panel on Musculoskeletal Imaging. ACR Appropriateness Criteria: Chronic Foot Pain. J Am Coll Radiol.
- American Academy of Orthopaedic Surgeons. Bunions. OrthoInfo.
Related Articles
What a bunion X-ray measures before surgery, what a normal post-op X-ray looks like, how long the bone cut takes to heal, and which report findings need attention.
Questions to ask before bunion surgery: what your standing X-ray shows, which operation and why, recovery and weight-bearing, risks, and when not to operate.
What the numbers on your foot X-ray mean: hallux valgus angle, intermetatarsal angle, Meary's angle, calcaneal pitch and Böhler's angle, with normal ranges and how each is measured.
Understand your imaging before your next appointment
MRI, X-ray or CT from a CD, folder or ZIP. A PDF report or photos of the films work too.
Free to open and preview, no account needed. An optional AI report from $10 explains your images in plain language, with questions for your doctor.
Your raw files stay on this device. Only rendered images and minimal context are sent when you request an AI report.
Medical Disclaimer: This page is for informational and educational purposes only. It does not constitute medical advice, diagnosis, or treatment. AI-generated analysis may contain errors. Always consult a qualified healthcare professional for medical decisions. Full Disclaimer